XDR vs SIEM: Choosing the Right Detection Stack
They solve overlapping but different problems — one correlates telemetry it owns, the other ingests everything. Which you need depends on your estate and who operates it.
GuardsArm Team
Security Experts
A SIEM ingests logs from anything that produces them and lets you correlate and search. XDR collects deep telemetry from a vendor's own sensors — endpoint, identity, email, cloud — and correlates it for you, with detections written by the vendor.
The difference that matters: SIEM accepts anything and gives you less analysis; XDR analyses deeply but only what it collects.
Where each is genuinely stronger
| Need | Better fit | Why |
|---|---|---|
| Endpoint and identity detection | XDR | Deeper telemetry, vendor-maintained detections, faster to value |
| Ingesting a legacy clinical system's logs | SIEM | XDR will not have a sensor for it |
| Compliance log retention | SIEM | Retention and search across arbitrary sources |
| Automated cross-signal correlation | XDR | It is the core function |
| Medical device network behaviour | SIEM | Devices run no agent; you have flow data at best |
| Small team, limited tuning capacity | XDR | Detections arrive maintained |
| Custom detections for your own estate | SIEM | Full control over rule logic |
| Incident investigation across everything | SIEM | Everything is in one searchable place |
The medical device row is decisive in healthcare. No XDR vendor has a sensor for an infusion pump. That telemetry is network-derived and has to land somewhere that accepts arbitrary sources — see IoMT security.
Why most organisations end up with both
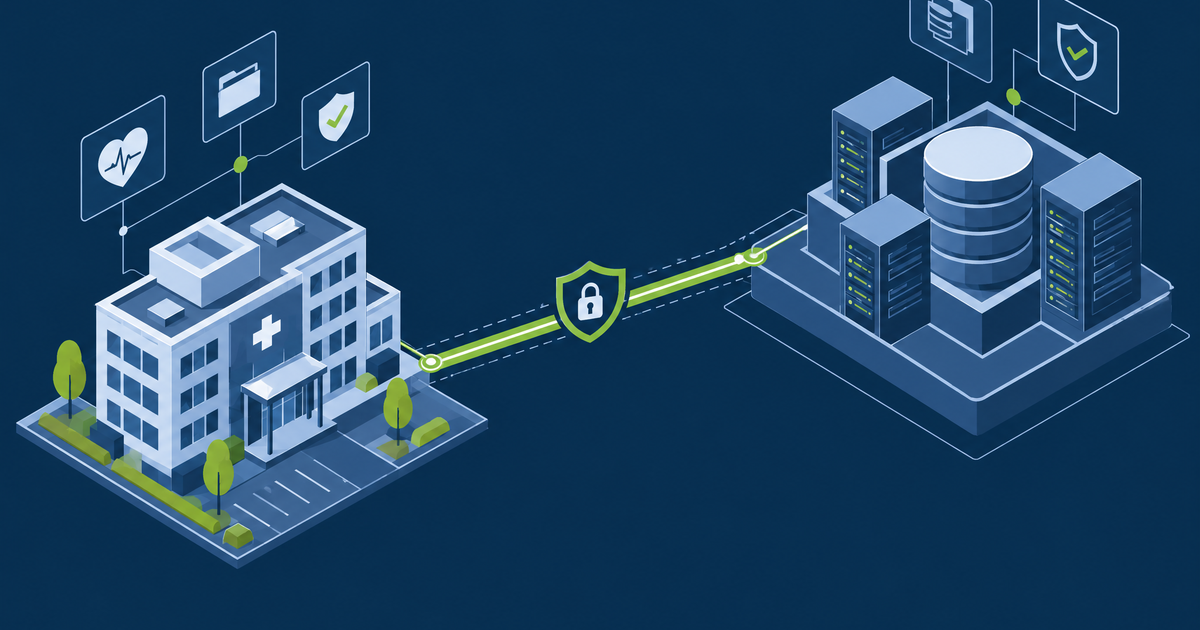
This is not a compromise so much as the correct architecture for a mixed estate. The mistake is buying XDR and decommissioning the SIEM, then discovering six months later that the clinical application logs, the firewall and the device telemetry have nowhere to go — and that compliance retention was being provided by the thing you turned off.
Questions that decide it
- Can the vendor's sensors cover the systems that matter to you? In a hospital, frequently not.
- What is your retention obligation, and does the platform meet it?
- Who writes and tunes detections — you, the vendor, or a provider?
- Can you export your data and your custom detections if you leave?
- What does it cost at your log volume in three years, not at onboarding?
The fourth question is the one skipped in procurement and the one that hurts at renewal.
Migration traps
Organisations replacing one with the other hit the same few problems:
- Log source coverage assumed, not verified. Confirm every current source has a path into the new platform before switching. Clinical and legacy systems are where this fails.
- Custom detections lost. Rules written over years in a SIEM rarely port. Inventory them and decide which matter before decommissioning.
- Retention gap at cutover. Running both briefly is expensive; having neither for a period is worse.
- Investigation across the boundary. During transition, evidence sits in two places. Document where to look for which period.
- Cost modelled at today's volume. Log volume grows; model three years.
If you are also deciding who operates it
That is a separate question from which tool, and usually the more important one — see build, buy or hybrid. A well-chosen platform with nobody watching it at 3am is not detection.
GuardsArm helps healthcare organisations select and operate detection platforms, including the clinical sources most stacks omit. Book a scoping call.
Written by GuardsArm Team
Our team of cybersecurity experts brings decades of combined experience in penetration testing, compliance auditing, and incident response. We're dedicated to helping organizations strengthen their security posture.
Take the next step on “XDR vs SIEM: Choosing the Right Detection Stack”
Talk to the GuardsArm team about how these services apply to your environment.